
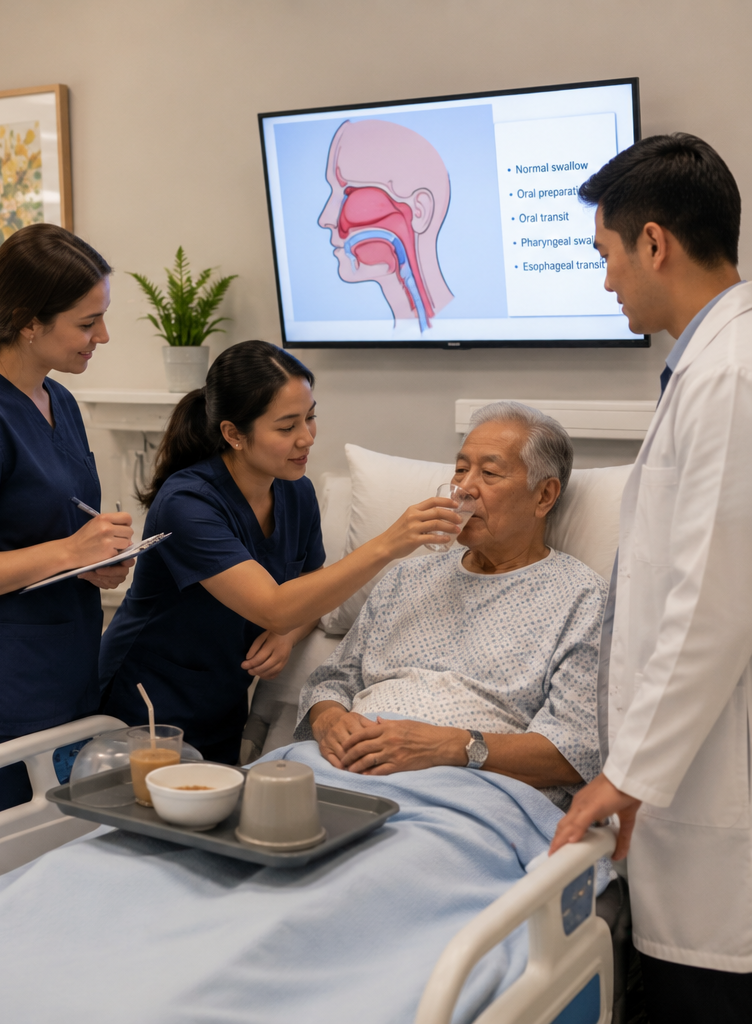
The phrase speech pathologist swallowing may sound surprising because many people associate speech-language pathologists only with communication. However, Canadian S-LPs also receive professional education in feeding and swallowing. They assess oropharyngeal dysphagia, recommend personalised strategies, contribute to instrumental examinations, and work with medical teams to support nutrition, hydration, respiratory health, comfort, and quality of life.
Oropharyngeal dysphagia is difficulty moving saliva, food, liquid, or medication through the mouth and throat. It can affect infants, children, adults, and older adults.
From my experience reviewing Canadian swallowing-care information, the most important distinction is between a general tip and an individual clinical recommendation. Advice such as thickening every drink, tucking the chin, or practising a popular online exercise can be inappropriate—and sometimes harmful—when the cause and physiology of the swallowing problem are unknown.
This guide explains what an S-LP does, when assessment is needed, and why treatment must be individualised. It is educational information, not a diagnosis or personal medical plan.
Featured answer: Speech pathologist swallowing care involves assessing and treating problems that affect moving saliva, food, liquids, or medication through the mouth and throat. An S-LP may complete a clinical examination, recommend instrumental testing, analyse swallowing physiology, suggest personalised strategies or exercises, and collaborate with medical, nursing, and nutrition professionals.
Table of Contents
- Why speech pathologists assess swallowing
- What dysphagia means
- Signs of a swallowing problem
- When swallowing difficulty is an emergency
- Causes of dysphagia
- The swallowing assessment process
- Screening versus clinical assessment
- VFSS and FEES compared
- Swallowing treatment options
- Thickened liquids and modified foods
- Dysphagia after stroke
- Swallowing care for children
- Dementia and progressive conditions
- The interprofessional dysphagia team
- What families can do
- Common swallowing-care myths
- People Also Ask
- Expert Q&A
- Conclusion
Why Does a Speech Pathologist Assess Swallowing?
Speaking and swallowing use many of the same structures, including the lips, tongue, jaw, soft palate, pharynx, larynx, and respiratory system. Therefore, speech-language pathology education includes anatomy, physiology, neurology, motor control, communication, feeding, and swallowing.
Speech-Language & Audiology Canada states in its position paper on swallowing and feeding disorders that S-LPs have specific expertise in evaluating and intervening in swallowing and feeding disorders across the lifespan.
The S-LP’s main area is oropharyngeal swallowing. This includes the oral and pharyngeal stages, as well as the coordination needed to protect the airway.
A speech-language pathologist may help answer questions such as:
- Can the person control food or liquid in the mouth?
- Is chewing effective?
- Does material move efficiently through the throat?
- Is material entering the airway?
- Does residue remain after the swallow?
- Does posture change swallowing performance?
- Does a different sip size help?
- Does the person need instrumental assessment?
- Is a swallowing exercise appropriate?
- How do cognition, breathing, fatigue, or positioning affect meals?
- How can eating and drinking remain as safe, comfortable, and meaningful as possible?
The S-LP does not manage every aspect alone. Swallowing care is usually interprofessional.
What Is Dysphagia?
Dysphagia is the medical term for difficulty swallowing.
The condition may affect the movement of:
- Saliva
- Food
- Water and other liquids
- Pills
- Crushed medication
- Nutritional supplements
- Tube-feeding-related secretions
Swallowing is commonly described in stages.
Oral preparatory stage
Food or liquid is received into the mouth. The person closes the lips, controls the material, and chews when needed.
Oral transport stage
The tongue moves the prepared material towards the back of the mouth.
Pharyngeal stage
The material travels through the throat. Several rapid events help direct it towards the esophagus while protecting the airway.
Esophageal stage
The material travels through the esophagus to the stomach.
Speech-language pathologists focus mainly on the oral and pharyngeal stages. Physicians and other medical specialists assess and manage many esophageal disorders.
However, symptoms can overlap. Therefore, the S-LP may recommend medical or gastrointestinal assessment when the concern appears to involve the esophagus.
Why Swallowing Problems Matter
Dysphagia can affect far more than whether someone coughs during a meal.
Potential consequences include:
- Dehydration
- Malnutrition
- Weight loss
- Reduced medication intake
- Airway invasion
- Respiratory complications
- Longer mealtimes
- Fatigue
- Fear of eating
- Reduced social participation
- Loss of favourite foods
- Caregiver stress
- Reduced quality of life
Food also has cultural, emotional, social, and spiritual importance. A meal may represent family, celebration, religion, community, comfort, or independence.
Therefore, good dysphagia care should not reduce a person to a risk score. The team must consider physiology, health, preferences, values, culture, and quality of life.
Signs You May Need Speech Pathologist Swallowing Assessment
One symptom does not confirm dysphagia. However, assessment may be appropriate when difficulties are new, persistent, worsening, or associated with health changes.
Possible signs include:
- Coughing during or after meals
- Choking
- A wet or gurgly voice after swallowing
- Food remaining in the mouth
- Difficulty chewing
- Food falling from the lips
- Repeated swallowing for one mouthful
- Taking much longer to finish meals
- Avoiding certain textures
- Complaining that food feels stuck
- Pain during swallowing
- Unexplained weight loss
- Dehydration
- Repeated chest infections
- Shortness of breath during meals
- Difficulty swallowing pills
- Drooling or trouble managing saliva
- Changes in eating after stroke or illness
- Refusal, distress, or fatigue during a child’s meals
- Reduced interest in eating
- Needing unusually small bites or sips
- Difficulty coordinating breathing and swallowing
Not everyone with aspiration coughs. Silent aspiration occurs when material enters the airway without an obvious cough or outward sign.
As a result, watching someone drink water at home cannot reliably rule out aspiration.
When Is Swallowing Difficulty an Emergency?
Call 911 when someone cannot breathe, speak, or cough effectively because the airway appears blocked. Begin appropriate choking first aid if you are trained, and follow emergency-dispatch instructions.
Sudden swallowing difficulty can also occur with stroke. Other stroke signs may include:
- Facial drooping
- Arm weakness
- Speech changes
- Sudden confusion
- Sudden balance problems
- Sudden severe headache
- Sudden vision changes
Call emergency services immediately when stroke is suspected. Do not give food, drink, or pills while waiting unless emergency professionals instruct you to do so.
Seek prompt medical help for:
- Inability to swallow saliva
- Rapidly worsening swallowing
- Food believed to be lodged
- Severe pain
- Breathing difficulty
- Signs of dehydration
- New swallowing problems after injury
- Significant allergic symptoms
- Repeated choking
- Possible aspiration with respiratory distress
HealthLink BC’s guidance on difficulty swallowing and dysphagia also advises medical assessment because swallowing difficulty may have several causes and can require different forms of treatment.
Common Causes of Swallowing Difficulties
Dysphagia is a symptom or condition with many possible causes.
Stroke
Stroke can affect sensation, movement, timing, attention, and coordination. Dysphagia may appear immediately and can change during recovery.
Traumatic brain injury
Brain injury may affect swallowing physiology, alertness, attention, impulse control, or the ability to follow strategies.
Parkinson’s disease
Parkinson’s disease may affect movement size, timing, coordination, cough strength, saliva management, and meal efficiency.
Dementia
Dementia can affect recognition of food, attention to meals, self-feeding, chewing, swallowing, and ability to communicate discomfort.
Multiple sclerosis and other neurological conditions
Neurological disease can affect strength, sensation, coordination, fatigue, and respiratory-swallowing timing.
Head and neck cancer
Cancer and its treatment may change oral or throat structures, sensation, saliva, pain, range of movement, and muscle function.
Critical illness
Intubation, mechanical ventilation, tracheostomy, weakness, and prolonged hospitalisation can contribute to swallowing difficulties.
Prematurity and developmental conditions
Infants and children may have difficulties coordinating sucking, swallowing, and breathing. Developmental, structural, sensory, motor, gastrointestinal, and medical factors may also affect feeding.
Age-related health changes
Age alone does not mean someone has dysphagia. However, older adults are more likely to experience medical and neurological conditions associated with swallowing problems.
Esophageal conditions
Reflux, narrowing, motility disorders, inflammation, and structural conditions may cause symptoms such as food sticking lower in the chest.
An S-LP may identify signs that warrant referral, but medical specialists evaluate many esophageal causes.
What Happens During a Speech Pathologist Swallowing Assessment?
A swallowing assessment may involve several stages. The exact process depends on the person’s medical stability, symptoms, age, setting, goals, and available services.
1. Referral and record review
The S-LP reviews relevant information, which may include:
- Medical diagnoses
- Medications
- Respiratory status
- Neurological history
- Recent surgery
- Weight changes
- Nutrition and hydration
- Previous swallowing reports
- Current food and drink textures
- Feeding assistance
- Client and caregiver concerns
2. Interview
The clinician asks about the person’s experience.
Questions may include:
- When did the problem begin?
- Is it getting worse?
- Which foods or drinks are difficult?
- Does food feel stuck?
- Is swallowing painful?
- Are meals tiring?
- Has there been coughing or choking?
- Has the person lost weight?
- What foods are culturally or personally important?
- What outcome matters most to the person?
The client’s report matters even when visible signs appear limited.
3. Oral-mechanism examination
The S-LP may examine the structures and movements involved in speech and swallowing.
This can include:
- Lips
- Tongue
- Jaw
- Soft palate
- Voice
- Cough
- Saliva management
- Dentition
- Oral hygiene
- Sensation
- Coordination
This examination provides useful information, but it cannot show the entire pharyngeal swallow.
4. Clinical swallowing trials
When appropriate, the S-LP may observe selected foods or liquids.
The clinician may consider:
- Positioning
- Alertness
- Breathing
- Lip closure
- Chewing
- Oral control
- Swallow timing
- Coughing
- Voice changes
- Residue
- Fatigue
- Mealtime duration
- Response to selected strategies
Trials should be chosen carefully. A routine water test may not be appropriate for every person.
5. Decision about instrumental assessment
The S-LP decides whether further visual assessment is needed to understand physiology, airway invasion, or the effect of strategies.
Screening, Clinical Assessment, and Instrumental Testing
These terms should not be used interchangeably.
| Process | Main purpose | What it can show | Key limitation |
| Swallowing screening | Identifies possible risk and need for referral | Basic signs or risk indicators | Does not diagnose the physiology |
| Clinical swallowing examination | Reviews history, oral function, trials, and visible clinical signs | Current function and reasons for concern | Cannot directly see the pharyngeal swallow |
| VFSS | Uses moving X-ray images during swallowing | Timing, movement, residue, and airway invasion across tested items | Uses radiation and samples a limited period |
| FEES | Uses a flexible endoscope to view the throat before and after swallows | Secretions, anatomy, residue, and airway findings | Does not directly show the oral stage or the swallow during brief “white-out” |
| Esophageal testing | Evaluates suspected esophageal problems | Depends on the medical procedure | Outside the primary oropharyngeal focus of S-LP assessment |
A bedside or clinical examination is valuable. However, it is not a perfect substitute for instrumental testing.
In particular, silent aspiration may not produce coughing, wet voice, or another clear bedside sign.
Videofluoroscopic Swallowing Study
A videofluoroscopic swallowing study is often shortened to VFSS. It may also be called a modified barium swallow study.
During VFSS:
- The person consumes selected materials containing barium.
- Moving X-ray images record the swallow.
- Different volumes or textures may be tested.
- The team may trial selected positions or strategies.
- The recording can be reviewed in detail.
The study may help identify:
- Oral control
- Timing
- Movement of swallowing structures
- Penetration
- Aspiration
- Residue
- Efficiency
- Response to strategies
- Suitable treatment targets
Penetration means material enters the space above the vocal folds. Aspiration means material passes below them into the airway.
VFSS is often completed with an S-LP and medical-imaging professionals. Specific roles depend on local policy and provincial requirements.
Fiberoptic Endoscopic Evaluation of Swallowing
Fiberoptic endoscopic evaluation of swallowing is shortened to FEES.
A thin flexible scope is passed through the nose to view the throat. The person then eats or drinks selected materials.
FEES may allow the team to examine:
- Secretions
- Anatomy
- Vocal-fold movement
- Residue
- Penetration or aspiration before or after the swallow
- Fatigue across repeated trials
- Response to selected strategies
FEES does not use radiation. Therefore, it may support longer observation or repeat assessment in appropriate cases.
However, it does not show every part of swallowing. The oral stage is not directly visible, and the view is briefly obscured during the swallow itself.
VFSS Versus FEES
Neither test is automatically better.
| Factor | VFSS | FEES |
| Imaging method | Moving X-ray | Flexible endoscopic camera |
| Radiation | Yes | No |
| Oral stage view | Yes | Limited |
| Pharyngeal view | Yes | Yes, except during white-out |
| Secretions | Limited | Directly visible |
| Real food options | May be limited by barium preparation | Often allows a range of suitable foods |
| Portability | Usually radiology-based | May be completed at bedside where services allow |
| Repeated trials | Limited by radiation exposure and tolerance | May permit longer assessment |
| Best choice | Depends on the clinical question | Depends on the clinical question |
The S-LP and medical team select the test based on the person’s needs, health, setting, and clinical question.
Speech Pathologist Swallowing Treatment
Treatment is not one universal exercise program.
The plan should address the specific swallowing problem, the person’s goals, health status, ability to participate, and available evidence.
Treatment can include compensatory, rehabilitative, habilitative, environmental, preventive, and educational approaches.
Compensatory strategies
A compensatory strategy changes how the person eats or drinks without necessarily changing the underlying physiology long term.
Examples may include:
- Adjusting posture
- Controlling sip or bite size
- Changing pace
- Alternating food and liquid
- Using a specific swallowing manoeuvre
- Changing utensils
- Providing feeding assistance
- Modifying food or liquid
- Changing the environment
A strategy should be recommended only after appropriate assessment. For example, a chin-down position helps some swallowing patterns but may worsen others.
Rehabilitation exercises
Rehabilitation aims to improve or maintain aspects of swallowing function.
A program may target:
- Strength
- Range of movement
- Timing
- Coordination
- Endurance
- Airway protection
- Cough
- Respiratory-swallowing coordination
Exercises must match the underlying impairment. An exercise that is useful for one person may be ineffective or inappropriate for another.
Habilitation
Habilitation focuses on developing a skill that has not yet been established. This is especially relevant for infants and children learning feeding and swallowing skills.
Education and partner training
The S-LP may educate the client, family, and care team about:
- Signs of difficulty
- Positioning
- Recommended assistance
- Pacing
- Oral care
- Equipment
- Emergency procedures
- When to stop a meal
- How to follow an individual plan
Consistency is important. A safe plan cannot help if different caregivers interpret it differently.
Thickened Liquids and Texture-Modified Foods
Thickened liquids move differently from thin liquids and may improve swallowing safety or control for some people.
However, they are not a universal solution.
Potential concerns include:
- Reduced fluid intake
- Dislike of the texture
- Reduced quality of life
- Incorrect preparation
- Medication interactions
- Increased residue for some people
- Inconsistent thickness
- Cost
- Difficulty accessing suitable products
Likewise, softer or texture-modified food may help some people but reduce food choice and enjoyment.
A recommendation should be based on the individual’s swallowing physiology, medical needs, preferences, and response during assessment.
Do not thicken drinks at home based only on coughing. Coughing may have several causes, while silent aspiration may occur without coughing.
Canadian facilities may use the International Dysphagia Diet Standardisation Initiative framework, known as IDDSI, to describe food textures and drink thickness. Staff still need training to prepare and test items correctly.
Dysphagia After Stroke
Swallowing difficulty is common after stroke and may affect safety, nutrition, hydration, medication, and recovery.
Canadian Stroke Best Practices recommends that people with acute stroke have swallowing screening completed as early as possible before oral intake. Those who fail screening or show swallowing concerns should receive a comprehensive assessment.
The current Canadian Stroke Best Practices dysphagia recommendations also address nutrition, oral care, assessment, and interdisciplinary management.
The process may include:
- Keeping the person from eating or drinking until screening when required
- Completing validated screening by trained staff
- Referring for S-LP assessment when risk is identified
- Using instrumental assessment when clinically indicated
- Developing an individual management plan
- Monitoring nutrition and hydration
- Providing oral care
- Reassessing when health or function changes
Family members should not give water or food to someone awaiting post-stroke swallowing assessment unless the clinical team approves it.
Silent Aspiration
Silent aspiration means material enters the airway without an obvious cough.
This can happen when sensation is reduced or the cough response is impaired.
A person may appear to swallow comfortably while aspiration occurs. Consequently:
- No coughing does not prove safety.
- A clear voice does not rule out aspiration.
- Pulse oximetry alone does not diagnose aspiration.
- Listening to the neck cannot directly show airway invasion.
- A successful single sip does not establish safety for a full meal.
Instrumental assessment may be needed when the clinical question cannot be answered at bedside.
Pneumonia Risk Is Multifactorial
Aspiration does not automatically lead to pneumonia. Likewise, pneumonia is not caused only by food or liquid entering the airway.
Risk may be influenced by:
- Oral bacteria
- Oral hygiene
- Immobility
- Dependence for feeding
- Reduced cough
- Respiratory disease
- Immune status
- Frailty
- Amount and type of aspirated material
- Overall medical condition
This is why oral care is an important part of dysphagia management.
A swallowing plan should address the whole person rather than focusing only on liquid thickness.
Speech Pathologist Swallowing Care for Infants and Children
Paediatric feeding and swallowing involves more than whether a child can swallow safely.
Feeding includes:
- Hunger and appetite
- Positioning
- Sucking
- Breast or bottle feeding
- Chewing
- Cup drinking
- Texture progression
- Sensory experience
- Mealtime interaction
- Self-feeding
- Family routines
A child may have a feeding disorder without dysphagia. Conversely, a child may have both.
Possible signs include:
- Coughing or colour changes during feeding
- Difficulty coordinating sucking, swallowing, and breathing
- Very long feeds
- Poor weight gain
- Frequent respiratory illness
- Distress at meals
- Limited texture progression
- Gagging
- Food refusal
- Chewing difficulty
- Fatigue
- Dependence on a narrow range of foods
Paediatric feeding concerns may require input from S-LPs, physicians, dietitians, occupational therapists, nurses, lactation professionals, psychologists, and other specialists.
Parents should not be blamed. Feeding difficulties are complex and may involve medical, nutritional, skill-based, developmental, sensory, and psychosocial factors.
Swallowing Care in Dementia
Dementia can affect:
- Recognising food
- Initiating eating
- Attention to meals
- Chewing
- Swallowing
- Self-feeding
- Communication of discomfort
- Decision-making
Management may involve environmental support, food presentation, positioning, feeding assistance, oral care, and consideration of personal preferences.
As dementia progresses, decisions can become ethically complex. The team may discuss aspiration risk, comfort, hydration, nutrition, tube feeding, and the person’s known wishes.
The goal is not simply to eliminate every risk. It is to make informed, person-centred decisions that consider comfort, dignity, values, and quality of life.
Progressive Neurological Conditions
Conditions such as Parkinson’s disease, amyotrophic lateral sclerosis, multiple sclerosis, and other neurological disorders can cause changing swallowing needs.
Early referral may allow time to:
- Establish a baseline
- Educate the person and family
- Monitor change
- Introduce exercises when appropriate
- Discuss future options
- Coordinate communication and swallowing plans
- Consider respiratory health
- Plan for changing support needs
Not every exercise is appropriate for every progressive condition. The clinician must consider fatigue, prognosis, respiratory function, and medical advice.
The Interprofessional Dysphagia Team
Swallowing care may involve:
- Speech-language pathologists
- Physicians
- Nurses
- Dietitians
- Occupational therapists
- Physiotherapists
- Respiratory therapists
- Pharmacists
- Dentists
- Dental hygienists
- Radiologists
- Medical radiation technologists
- Gastroenterologists
- Otolaryngologists
- Personal support workers
- Family members
- The client
Each member contributes different expertise.
The S-LP
Assesses oropharyngeal swallowing, recommends appropriate testing, interprets physiology within professional competence, and develops behavioural or compensatory plans.
The physician
Evaluates medical causes, diagnoses medical conditions, manages disease, and coordinates relevant procedures or referrals.
The dietitian
Assesses nutritional and hydration needs, intake adequacy, supplements, and dietary planning.
Nursing staff
Monitor day-to-day changes, administer medication, support meals, and communicate clinical observations.
Occupational therapy
May address self-feeding, seating, upper-limb function, sensory needs, equipment, and environmental access.
Pharmacy
Helps evaluate medication formulation, crushing restrictions, interactions, and alternative administration options.
Tablets should not be crushed without confirming that the medication can safely be altered.
What Families Can Do While Waiting for Assessment
Contact the medical team for individual advice. Meanwhile:
- Record what happens. Note the food or liquid, time, symptoms, and relevant health changes.
- List medications and diagnoses. Bring current information to appointments.
- Describe the usual meal. Include duration, position, assistance, and food textures.
- Report weight or hydration changes. These may affect urgency.
- Maintain recommended oral care. Follow the person’s dental or medical plan.
- Follow existing professional recommendations. Do not alter textures independently.
- Avoid unprescribed swallowing exercises. The wrong exercise may be ineffective or harmful.
- Do not force intake. Stop and seek guidance when the person shows distress.
- Prepare questions. Ask what the team knows, what remains uncertain, and whether instrumental testing is needed.
- Know emergency signs. Call 911 for airway obstruction or suspected stroke.
Questions to Ask the Swallowing S-LP
Useful questions include:
- Which stage of swallowing appears affected?
- What information is still missing?
- Is instrumental assessment needed?
- Why was VFSS or FEES selected?
- Was silent aspiration considered?
- What is the goal of each strategy?
- What are the benefits and burdens of texture modification?
- How will hydration be monitored?
- Which exercises target the identified impairment?
- How often should the plan be practised?
- When will swallowing be reassessed?
- What signs should trigger medical review?
- How should pills be taken?
- Who should train family or staff?
- How were the client’s preferences considered?
A good recommendation should have a clear reason.
Common Speech Pathologist Swallowing Myths
Myth 1: Speech therapists only work on speech
Canadian S-LPs are educated in communication, feeding, and swallowing.
Myth 2: Coughing always means aspiration
Coughing may indicate airway irritation or another issue. Assessment is needed to determine what is happening.
Myth 3: No coughing means swallowing is safe
Silent aspiration can occur without a cough.
Myth 4: Thickened drinks are always safer
They may help some people, but they also have limitations and can worsen efficiency or reduce intake.
Myth 5: Everyone should tuck their chin
Postural strategies have different effects on different swallowing patterns.
Myth 6: A bedside assessment can see aspiration
A clinical examination observes signs and function. It does not directly visualise the pharyngeal swallow.
Myth 7: Tube feeding eliminates aspiration risk
People can aspirate saliva or refluxed material. Tube feeding also has benefits, burdens, and medical considerations.
Myth 8: Dysphagia is a normal part of ageing
Healthy ageing can change swallowing, but persistent difficulty should not be dismissed solely because someone is older.
People Also Ask About Speech Pathologist Swallowing Care
Can a speech pathologist help with swallowing?
Yes. S-LPs have specialised education in oropharyngeal swallowing and may assess dysphagia, recommend instrumental testing, develop individual strategies, provide rehabilitation, and train families or care staff.
What swallowing test does a speech pathologist do?
An S-LP may complete a clinical swallowing examination and participate in VFSS or FEES. The best method depends on the person’s symptoms, medical condition, setting, and clinical question.
What are signs of aspiration?
Possible signs include coughing, choking, wet voice, breathing changes, or distress during meals. However, silent aspiration may cause no obvious sign, so assessment may require instrumental imaging.
Should I thicken liquids when someone coughs?
Not without individual clinical advice. Thickening may help some swallowing patterns but create other problems, including reduced intake or increased residue.
When should dysphagia be assessed?
Seek assessment when swallowing difficulty is persistent, worsening, associated with weight loss or respiratory illness, or appears after a neurological or medical event. Call 911 for airway obstruction or suspected stroke.
Expert Q&A About Dysphagia Assessment
1. Can an S-LP diagnose the cause of every swallowing problem?
No. An S-LP assesses oropharyngeal function within professional scope, but medical conditions and esophageal causes may require physicians, imaging, gastroenterology, otolaryngology, or other services.
2. How often should swallowing be reassessed?
There is no universal schedule. Reassessment may be needed after a health change, improvement, decline, new respiratory concern, weight loss, altered alertness, or difficulty following the current plan.
3. Can swallowing therapy restore normal eating?
Some people improve substantially, while others need long-term strategies or changing support. Outcomes depend on the cause, physiology, health, treatment response, and personal goals; guarantees are not appropriate.
4. Can dysphagia assessment be completed virtually?
Parts of history-taking, observation, education, and follow-up may be possible virtually in suitable cases. However, telepractice cannot replace every physical or instrumental assessment, and emergency planning is essential.
5. Can a person choose to eat despite known aspiration risk?
Capable individuals generally participate in informed decisions about their care. The team should explain benefits, risks, uncertainties, and alternatives while considering goals and quality of life; individual legal or capacity questions require appropriate professional review.
Conclusion: Swallowing Care Must Be Individualised
Professional speech pathologist swallowing care does much more than watch someone take a sip of water. It connects medical history, client experience, oral examination, mealtime observation, instrumental evidence, physiology, nutrition, respiratory health, and personal goals.
An S-LP may:
- Identify signs of oropharyngeal dysphagia
- Complete a clinical swallowing examination
- Recommend VFSS or FEES
- Analyse swallowing physiology
- Trial appropriate strategies
- Develop personalised exercises
- Advise on texture or equipment when justified
- Educate families and care teams
- Monitor change
- Refer to other professionals
However, no single strategy works for everyone. Thickened liquids, posture changes, modified foods, and swallowing exercises can have different effects depending on the impairment.
Seek urgent emergency help when a person cannot breathe, speak, or cough effectively, or when sudden swallowing difficulty occurs with possible stroke signs. For ongoing concerns, contact a physician or qualified S-LP rather than relying on general online exercises.
For more Canadian communication and swallowing information, explore Speech For All’s person-centred speech-language pathology resources.
Tags: speech and language therapist swallowing, speech and language therapist swallowing assessment, speech pathologist swallow study, speech pathologist swallowing, speech pathologist swallowing assessment, speech pathologist swallowing disorders, speech pathologist swallowing near me, speech pathologist swallowing test, speech pathologist swallowing therapy, speech pathology swallowing exercises